
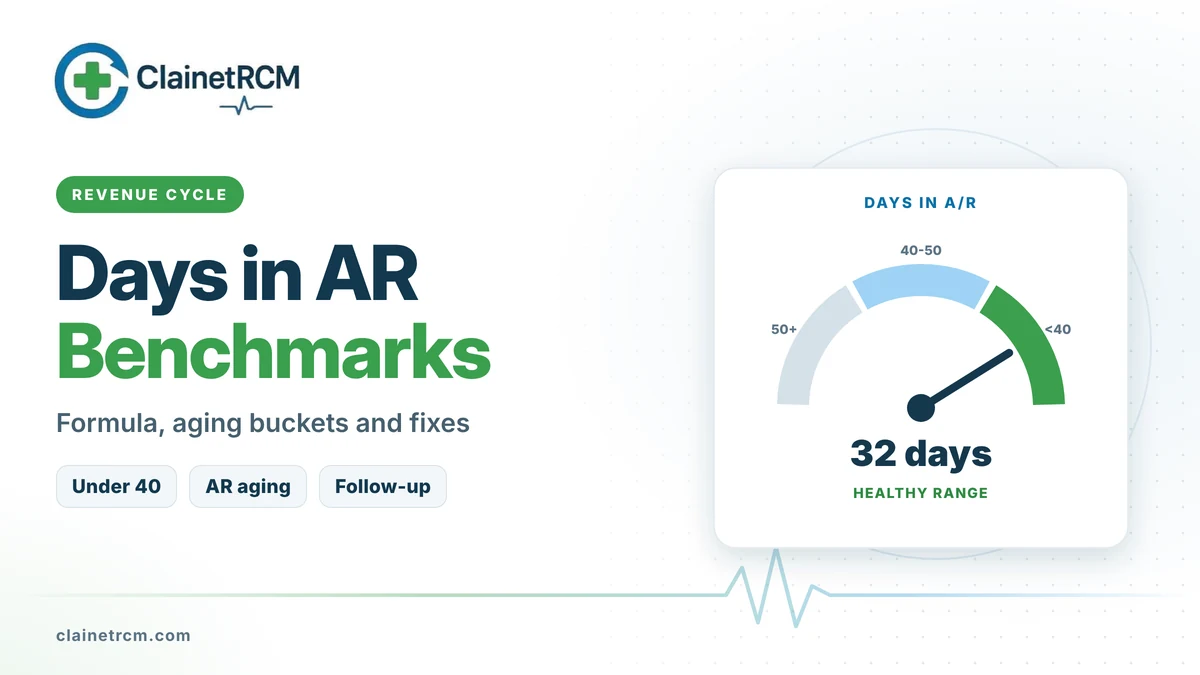
Days in AR (days in accounts receivable) is the average number of days it takes your practice to get paid after a service is billed. It is the fastest single read on cash flow. When the number climbs, claims are stalling somewhere between the front desk, the coder, the payer and the patient. This guide gives you the formula, the benchmarks most practices aim for, how to read AR aging buckets and a follow-up routine that brings the number down.
Quick answer: Divide your total accounts receivable by your average daily charges. Average daily charges are your gross charges for a recent period, often the last three months, divided by the number of days in that period. Most physician practices aim to keep days in AR under 40, and strong performers stay near or below 30. Specialty, payer mix and claim complexity all move the target, so compare yourself with similar practices and watch the trend month to month.
How to Calculate Days in AR
- Find total AR. Pull total outstanding receivables at month end, insurance and patient balances together. Report credit balances separately so they do not hide old debt.
- Find average daily charges. Add gross charges for the last three months and divide by the number of days in those months (about 90). Some practices use 6 or 12 months to smooth out seasonal swings.
- Divide. Total AR divided by average daily charges equals days in AR.
Example: A practice has $240,000 in total AR. It billed $720,000 in gross charges over the last 90 days, so average daily charges are $8,000. Days in AR is $240,000 ÷ $8,000 = 30 days.
Gross vs net days in AR
The standard formula uses gross charges because every billing system can report them. MGMA also describes a net version that divides AR by net patient revenue per day (annual net patient revenue divided by 365). The net version is more realistic when your fee schedule sits far above what payers allow. Either version works, as long as you calculate it the same way every month and never compare a gross figure with someone else’s net figure.
Days in AR Benchmarks
| Days in AR | What it usually means |
|---|---|
| Under 30 | Excellent: claims go out clean and follow-up is tight |
| 30 to 40 | Healthy for most physician practices |
| 40 to 50 | Needs attention: look for denials, held claims and slow payers |
| Over 50 | A cash flow problem: aged claims are at risk of timely filing write-offs |
Industry guidance commonly cited from MGMA puts the target under 40 days for physician groups, with high performers below 30. Context matters. Surgical specialties that depend on prior authorizations, anesthesia groups, and practices with heavy workers’ compensation, auto or out-of-network volume often run longer. Practices with many small, routine claims usually run shorter. Rising patient responsibility from high-deductible plans also pushes the number up, because patient balances take longer to collect than payer balances.
Reading AR Aging Buckets
Days in AR tells you how fast money moves overall. AR aging tells you where it is stuck. Sort every open balance by age from the date of service or the date of the first claim submission, and keep that choice consistent.
| Aging bucket | What usually sits there | What to aim for |
|---|---|---|
| 0 to 30 days | New claims in normal payer processing | The largest share of your AR |
| 31 to 60 days | Claims that should pay soon; first follow-up is due | Shrinking each month |
| 61 to 90 days | Problem claims: denials, pends, missing information | A small share |
| 91 to 120 days | Appeals and corrected claims in progress | Many practices keep AR over 90 days under about 15% of total AR |
| Over 120 days | Claims at high risk of timely filing loss | Under about 10% is a common goal |
Split the report by payer and by financial class. A healthy total can hide one payer whose claims all sit past 90 days, and patient balances age very differently from insurance balances.
Why Days in AR Goes Up
- Eligibility and registration errors. Wrong member IDs, inactive coverage and missing secondary insurance lead to denials that restart the clock.
- Coding and modifier errors. Bundling edits, missing modifiers and unsupported diagnosis codes send claims back for correction.
- Charge lag. Visits that sit unbilled for a week add a week to every claim before the payer even sees it.
- Credentialing gaps. Claims held for a provider who is not yet enrolled can sit for months.
- Unworked rejections and denials. Clearinghouse rejections that nobody fixes never become claims at all.
- Slow or troubled payers. Payer system problems, medical record requests and pended claims stretch payment times.
- Patient balances. Statements that go out late, or only by mail, slow patient collections.
- Posting backlogs. Payments received but not posted make AR look larger than it is.
A Follow-Up Routine That Lowers Days in AR
Every day
- Enter charges within one to two business days of the visit to keep charge lag low.
- Work clearinghouse rejections the same day they arrive.
- Post ERAs and deposits daily and route denials straight to a work queue.
Every week
- Run payer follow-up on claims with no response after 21 to 30 days, using payer portals or electronic claim status checks.
- Work denials by dollar value and appeal deadline, not by the order they arrived.
- Send patient statements on a fixed cycle, with text and email payment links.
Every month
- Review AR aging by payer, provider and location.
- Recalculate days in AR with the same formula and period.
- Rank denials by reason code and fix the top causes at the front end.
- Review credit balances and refund overpayments within the time your payer contracts and state rules require.
Mistakes That Distort the Number
- Writing off to look better. Large write-offs shrink AR and make days in AR look healthy while revenue is lost. Track adjustments by reason and watch your net collection rate alongside days in AR.
- Mixing gross and net figures from one month to the next.
- Netting credit balances against debit balances, which hides old unpaid claims.
- Changing the measurement period without restating earlier months.
- Ignoring accounts sent to collections. Report days in AR with and without them so trends stay comparable.
Example: From 52 Days to 34
Here is an illustrative case. A five-provider group found its days in AR at 52, with 18% of AR older than 120 days. Two causes stood out: a new nurse practitioner whose claims were held while payer enrollment was pending, and repeated rejections for missing referring provider details. The group finished enrollment and billed the held claims within each payer’s filing limit, added a front-desk referral check, and started daily rejection work. Within four months, days in AR fell to 34 and the share of AR over 120 days dropped below 10%.
Frequently Asked Questions
Most physician practices aim for under 40 days, and well-run practices often stay near 30 or lower. The right target depends on your specialty and payer mix, so track your own trend and compare against practices like yours.
Divide total accounts receivable by average daily charges. To get average daily charges, divide gross charges for the last three months by the number of days in those months.
They measure the same idea. Days sales outstanding (DSO) is the general business term, and days in AR is the term most medical practices use. Make sure both figures use the same inputs before you compare them.
Yes, include them in the total. Then report insurance AR and patient AR separately, because they age differently and need different follow-up.
Monthly is standard. Use the same formula, period and data source each time so the trend means something.
A very low figure is usually good news, but check that it is not the result of heavy write-offs or claims that were never billed. Pair it with your net collection rate and denial rate before you celebrate.
Final Thoughts
Days in AR is simple to calculate and hard to fake, as long as you measure it the same way every month and read it next to AR aging and write-offs. Fix the front-end errors that cause denials, bill quickly, and follow up on every unpaid claim before it ages past 90 or 120 days. If your team is short on time, our accounts receivable management services can work the backlog for you. You can also read our guide on how to improve patient collections to speed up the patient side of your AR.
Bring Your Days in AR Down
Our AR team works every unpaid and denied claim by age and dollar value, so cash comes in faster and nothing ages past a filing limit.
Get AR Recovery Help
Written by
ClainetRCM Billing Team
ClainetRCM is a Boston-based revenue cycle management company specializing in medical billing, coding, credentialing and denial management for healthcare providers across all 50 states. Our AAPC and AHIMA certified team works inside your existing EHR, files claims within 24 to 48 hours and reviews every AR bucket on a 14-day cycle.


