Pulmonary function test CPT codes describe each part of a lung function study: spirometry, bronchodilator response, lung volumes, diffusing capacity and exercise testing. A full PFT lab study is usually reported with several codes, but many components are bundled into others, and Medicare’s edits are strict. Knowing which combinations are allowed is the key to getting a complete study paid.
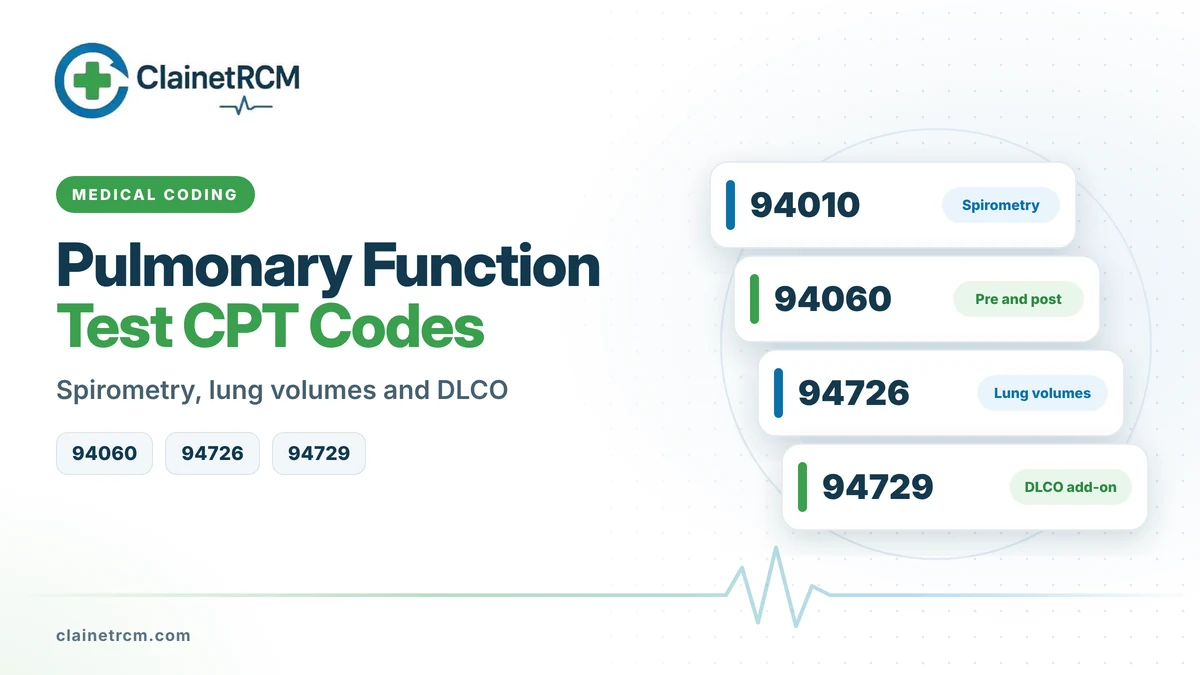
Quick answer: Report spirometry with 94010, or 94060 when spirometry is performed before and after a bronchodilator; never both on the same day. Lung volumes are reported with 94726 (plethysmography) or 94727 (gas dilution or washout), and airway resistance by oscillometry with 94728. Diffusing capacity (DLCO) is the add-on 94729, reported with a primary PFT code. A six-minute walk test is 94618. Flow-volume loops (94375), maximal voluntary ventilation (94200), the bronchodilator treatment in 94060 (94640) and pulse oximetry (94760) are generally not paid separately with spirometry.
Pulmonary Function Test CPT Codes
| Code | Description | Notes |
|---|---|---|
| 94010 | Spirometry | Includes vital capacity and flow-volume loop when performed |
| 94060 | Bronchodilation responsiveness: spirometry before and after a bronchodilator | Includes 94010 and the bronchodilator treatment |
| 94070 | Bronchospasm provocation evaluation with multiple spirometric determinations | For example, methacholine challenge |
| 94726 | Plethysmography for lung volumes and, when performed, airway resistance | Body box testing |
| 94727 | Gas dilution or washout for lung volumes | Not reported with 94726 |
| 94728 | Airway resistance by oscillometry | Not reported with 94010, 94060 or 94726 |
| 94729 | Diffusing capacity (add-on) | Requires a primary PFT code |
| 94618 | Pulmonary stress testing, such as a six-minute walk | Includes oximetry |
| 94617 | Exercise test for bronchospasm with ECG recording | Pre- and post-exercise spirometry included |
| 94621 | Cardiopulmonary exercise testing | Includes measurement of oxygen uptake and expired gases |
| 95012 | Exhaled nitric oxide measurement | Often used in asthma evaluation |
Bundling Rules That Cause Denials
- 94010 with 94060 or 94070. Both of those codes include spirometry, so 94010 is never billed with them on the same date.
- 94375, 94150 and 94200 with spirometry. Flow-volume loops, vital capacity and maximal voluntary ventilation are included in 94010 and 94060.
- 94640 with 94060. The bronchodilator treatment given during bronchodilator responsiveness testing is part of 94060.
- Two lung volume methods. Report either 94726 or 94727, not both, unless the payer allows both for distinct, documented reasons. Code 94726 already includes airway resistance when performed, so 94728 is not added to it.
- Pulse oximetry. Medicare does not pay 94760 or 94761 separately when other services are billed the same day.
- 94729 alone. DLCO is an add-on and must be reported with a primary code such as 94010, 94060, 94726, 94727 or 94728.
Exercise and Challenge Testing
Exercise and challenge codes are chosen by what the test measures. A six-minute walk with oximetry is 94618. An exercise test for bronchospasm with pre- and post-exercise spirometry and ECG recording is 94617. Full cardiopulmonary exercise testing with measurement of oxygen uptake and expired gases is 94621. A methacholine challenge with repeated spirometry is 94070, and the provocative agent may be billed separately when the office supplies it. Some payers also pay the bronchodilator used in 94060, such as unit-dose albuterol, when the office supplies it, while others treat it as included, so check each payer’s policy.
Professional and Technical Components
Most PFT codes have a professional component (the interpretation and report) and a technical component (the equipment and respiratory therapist or technician). In the office, the practice bills globally. When testing is done in a hospital PFT lab, the interpreting physician bills with modifier 26 and the hospital bills the technical portion. See our guide to modifier 26 and TC for more.
Documentation Requirements
- The clinical indication, such as dyspnea, chronic cough, COPD follow-up or asthma evaluation
- Test quality, such as the number of acceptable and reproducible maneuvers
- Predicted values and the reference equations used
- The bronchodilator name and dose for 94060
- Results for each component performed
- A signed interpretation that answers the clinical question
Keep the raw data and flow-volume graphics with the report so a reviewer can confirm what was performed. Payers often limit how frequently PFTs are covered and do not cover routine preoperative testing without a clinical indication, so link each test to a supporting diagnosis, such as shortness of breath (R06.02), COPD (J44.9) or asthma (J45.-).
Example: Full PFT Study
A patient with progressive dyspnea has spirometry before and after albuterol, lung volumes by plethysmography, diffusing capacity and a six-minute walk test with oximetry.
- Codes: 94060, 94726, 94729 and 94618
- Not billed: 94010, 94375 and 94760, which are included
- Hospital setting: the physician adds modifier 26 to each code and the hospital bills the technical portion
Common Errors
- Billing 94010 and 94060 together
- Billing a flow-volume loop separately with spirometry
- Reporting both lung volume methods without payer approval
- Billing DLCO without a primary code
- Billing the global service when the test was performed in a hospital
- Missing the interpretation report, which supports the professional component
- Testing more often than the payer allows without documenting a change in symptoms or treatment
Frequently Asked Questions
Code 94010 is spirometry alone. Code 94060 is spirometry performed before and after a bronchodilator to measure the response, and it includes the spirometry and the bronchodilator treatment.
No. Diffusing capacity is an add-on code that must be reported with a primary pulmonary function code, such as spirometry or a lung volume code.
Generally no. Both measure lung volumes, so report the method used. Code 94726 also includes airway resistance when performed.
Medicare does not pay pulse oximetry separately when other services are billed on the same day, and many commercial payers follow the same rule.
Report 94618 for pulmonary stress testing, such as a six-minute walk with oximetry and oxygen titration when performed.
Final Thoughts
Pulmonary function test CPT codes pay well when every component is coded and nothing bundled is billed. Learn how we support lung care practices on our pulmonology billing page, or review diagnosis coding in our shortness of breath ICD-10 guide.
Stop PFT Bundling Denials
Our pulmonology coders match every PFT component to the right code and apply NCCI edits before claims go out, so full lab studies are paid as performed.
Get Pulmonology Coding Help
Written by
ClainetRCM Billing Team
ClainetRCM is a Boston-based revenue cycle management company specializing in medical billing, coding, credentialing and denial management for healthcare providers across all 50 states. Our AAPC and AHIMA certified team works inside your existing EHR, files claims within 24 to 48 hours and reviews every AR bucket on a 14-day cycle.